Introduction
Osteoarthritis (OA) is the most common type of arthritis. It is marked by gradual degenerative changes that affect not only the articular cartilage but the whole joint structure, including the subchondral bone and the synovial membrane [1,2]. Many pathological alterations are evident in joints affected by OA, among them degeneration of the articular cartilage, thickening of the subchondral bone, formation of osteophytes, varying levels of synovial inflammation, degeneration of the ligaments and knee menisci, and hypertrophy of the knee capsule [1]. Osteoarthritis causes pain, swelling and stiffness and difficulty in moving the affected joint; as movement is reduced, muscles lose strength and people become less able to perform physical activities [3]. The risk factors most strongly associated with OA are increasing age, female sex, obesity, previous joint injury, genetic factors, malalignment and abnormal joint morphology [1,2].
1.1 Background
Osteoarthritis is an important cause of disability worldwide, although estimates vary with the population studied and the definition used; research in the United Kingdom has described trends in its incidence and prevalence [4]. An analysis of Global Burden of Disease 2017 data reported 303.1 million prevalent cases of hip and knee osteoarthritis worldwide in that year [5], and the World Health Organization reports that 528 million people were living with osteoarthritis in 2019 [3]. These estimates come from different assessment rounds and are not directly comparable.
A cross-sectional study of knowledge and awareness of osteoarthritis and its risk factors in the Hail region of Saudi Arabia, conducted in 2023, found that about 59.1% of participants had poor knowledge of OA, and its authors recommended wider public education [6].
The present study assessed knowledge of osteoarthritis and its risk factors among adults in Bisha, Saudi Arabia, in order to identify the misconceptions most in need of attention in local health education.
2. Subjects and Methods
2.1 Study design and participants
This descriptive cross-sectional study was conducted among adults in Bisha, Saudi Arabia, during 2024–2025. Eligible participants were residents of Bisha aged 18 years or older who provided informed consent. Individuals younger than 18 years, those living outside Bisha and those who did not consent were ineligible.
2.2 Sample size
The sample size was calculated with the Raosoft online sample size calculator [7] and estimated at a minimum of 384, using a 5% margin of error, a 95% confidence level, a population size of 202,096 (the population reported for Bishah governorate in the 2022 Saudi census [8,9]) and a 50% response distribution. The final sample included 442 respondents.
2.3 Sampling and recruitment
Convenience sampling was used. The self-administered online questionnaire was distributed to residents of Bisha through social media and WhatsApp.
2.4 Questionnaire
An Arabic, self-administered questionnaire was used. Its content addressed themes examined in earlier Saudi research on OA awareness [10]. It comprised three sections covering demographic characteristics, general knowledge of OA, and 17 questions on causes, symptoms, risk factors, diagnosis and management. Responses to the knowledge items were summarized as frequencies and percentages.
2.5 Knowledge classification
Overall knowledge was classified as high (211 participants) or low (231 participants), and these categories were used for exploratory comparisons by sex, age and education.
2.6 Statistical analysis
Data were entered into Excel for cleaning and analyzed with SPSS Statistics version 26. Categorical variables were described using frequencies and percentages. Unadjusted associations between demographic characteristics and knowledge categories were examined with Pearson’s chi-square test. A p-value below 0.05 was considered statistically significant.
2.7 Ethical approval and consent
Ethical approval was obtained from the Ethics and Research Committee of the College of Medicine, University of Bisha, reference UB-RELOC H-06-BH-087/(01/05/47). Participants provided informed consent before completing the questionnaire, and those who did not consent did not proceed. Confidentiality was maintained.
4. Discussion
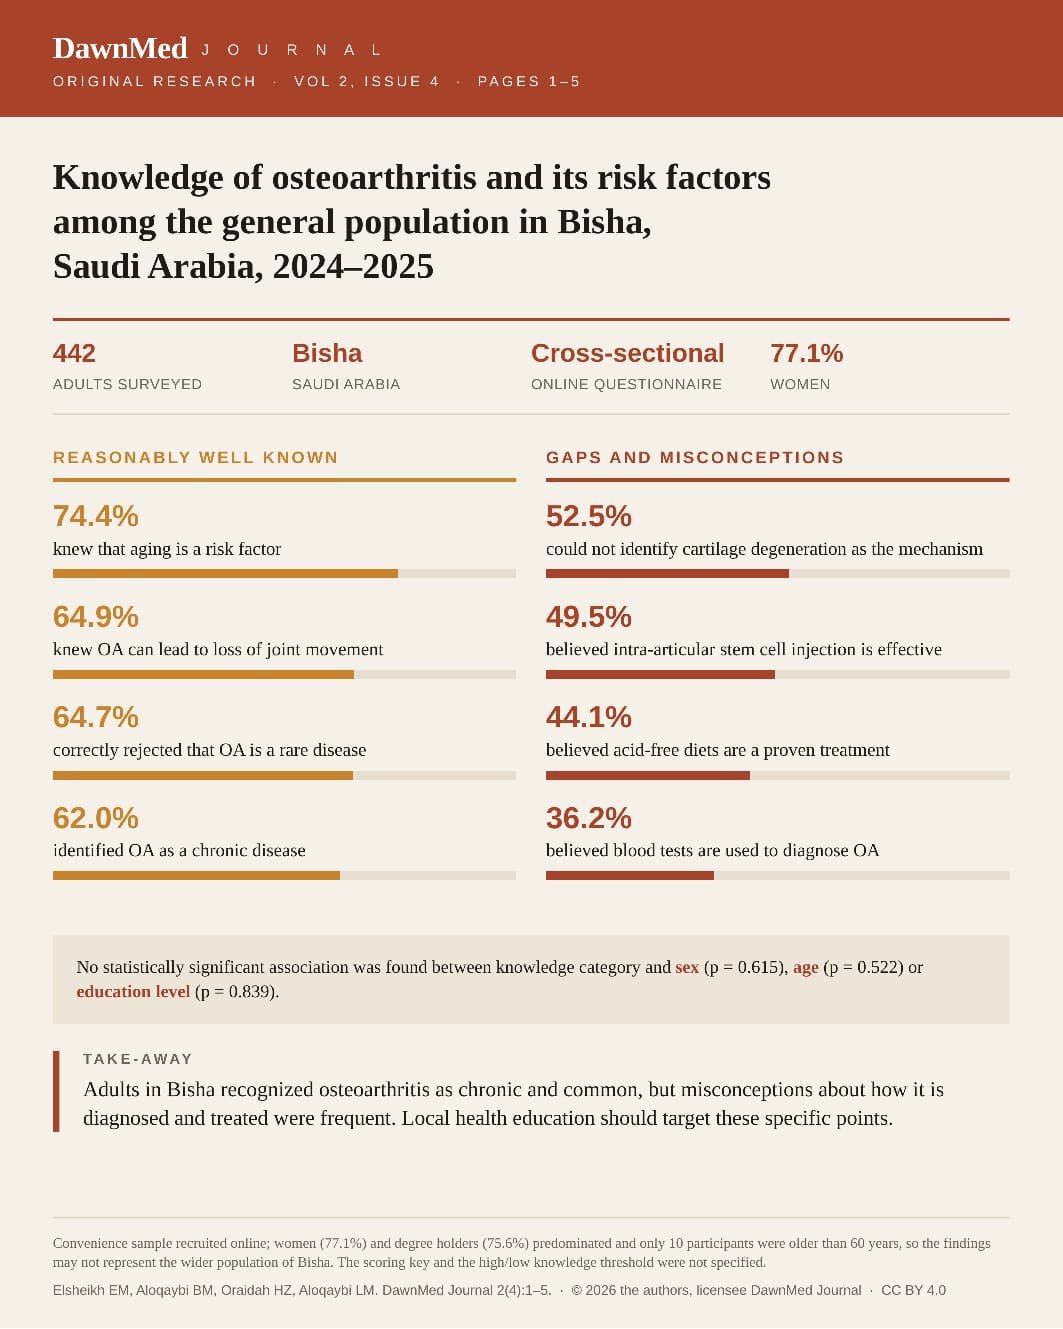
Adults surveyed in Bisha showed uneven knowledge of osteoarthritis. Most recognized the disease as chronic and common and identified aging as a risk factor, but fewer than half identified the underlying mechanism, and misconceptions about diagnosis and treatment were frequent. Comparable surveys have been reported from other Saudi regions [11], including one in Hail whose authors recommended wider public education [6].
Nearly half the sample (48.0%) reported a family member who had been diagnosed with OA, which reflects familiarity with the disease rather than its prevalence. Alahmed et al. reported that 13.6% of participants in Hail had themselves been diagnosed with osteoarthritis and that 40.3% knew someone with the disease, an item broader than the family-specific question used here [6].
The mechanism of osteoarthritis was correctly identified by 47.5% of participants, close to the 54.16% reported by Alkalash et al. in Al-Qunfudah, Saudi Arabia, for the item on the underlying mechanism of the disease [12]. Osteoarthritis was correctly identified as chronic by 62.0%, and 64.7% correctly rejected the statement that it is rare, while 14.3% considered it rare and 21.0% were unsure. Most respondents therefore recognized that OA is common, although one in five remained uncertain. In the same Al-Qunfudah survey, 49.60% classified OA as chronic and 74.53% acknowledged it as a common disease, a higher proportion than in the present study [12].
Joint pain was known not to be the only symptom by 48.4% of participants, while 64.5% recognized joint stiffness and 57.2% recognized joint swelling and inflammation as manifestations of OA. Loss of joint mobility was correctly reported as a consequence of OA by 64.9%. Salih et al. found a similar pattern in a survey of knee osteoarthritis in the United Arab Emirates, where 51.0% were aware that joint pain is not the only symptom, 52.1% knew that joint stiffness is a sign of the disease, and 65.8% answered that osteoarthritis may lead to loss of joint movement [13]. That survey also asked about muscle weakness, recognized by 54.5%, an item the present questionnaire did not include.
Genetics was recognized as a risk factor by 39.4% of participants, and 74.4% correctly answered that aging is a risk factor. Recognition of a genetic contribution is consistent with evidence that hereditary factors influence susceptibility to osteoarthritis, including inherited variation in joint shape [14]. Almoftery et al. reported similar figures among women attending the clinics of Aseer Central Hospital, where 43.17% believed that genetic factors could lead to OA and 65.47% said that aging is a factor in OA [15].
Physical examination and X-rays were identified as diagnostic methods by 58.8% of participants, and 36.2% believed that blood tests are used. Osteoarthritis can be diagnosed clinically and imaging is not routinely required [16], while blood tests serve to exclude other causes of symptoms rather than to confirm the diagnosis [17]. Responses on aspirin were divided: 27.4% answered yes, 27.8% answered no and 44.8% did not know. Alghamdi et al. in Makkah, Saudi Arabia, reported that 62.9% identified clinical examination and X-rays as diagnostic methods, while 45.6% answered that blood tests are not used for diagnosis and 33.0% were unsure; that survey asked about analgesics in general rather than aspirin, and 35.0% agreed that they could improve symptoms [18].
On management, 50.0% of participants were aware that exercise benefits people with osteoarthritis, and 44.1% believed that acid-free diets are an effective treatment. Physical therapy was thought to relieve symptoms by 293 participants (66.3%), intra-articular stem cell injection was considered effective by 49.5%, and 55.4% believed that joint replacement surgery is the final option for symptom relief. These are the beliefs respondents reported, and they can be set against current guidance: the 2019 American College of Rheumatology and Arthritis Foundation guideline recommends against stem cell injection for hip and knee OA [19], while the National Institute for Health and Care Excellence recommends considering referral for hip, knee or shoulder replacement when joint symptoms substantially affect quality of life and non-surgical management is ineffective or unsuitable [16]. Alyami et al. in Jeddah reported comparable figures, with 69.0% of participants believing that exercise such as swimming is beneficial and 52.6% that acid-free diets are a proven treatment [11].
No statistically significant association was found between knowledge category and sex, age or education level. These results do not establish equivalent knowledge across groups: the comparisons were unadjusted and some strata contained few participants.
4.1 Limitations
Participants were recruited online by convenience sampling, so the sample cannot be assumed to represent the adult population of Bisha, and the margin of error used in the sample size calculation assumes probability sampling. Women (77.1%) and holders of a bachelor’s degree (75.6%) predominated, only 10 participants were older than 60 years, and residents with limited internet access are likely to be underrepresented. Responses were self-reported and therefore open to recall and social desirability bias, and the cross-sectional design with unadjusted comparisons allows neither causal inference nor control for confounding. Several items, particularly those on acid-free diets, aspirin, blood tests and stem cell injection, may have been understood differently by different respondents, and the aspirin item did not distinguish symptom relief from treatment recommendations. Evidence on the measurement properties of the Arabic questionnaire was not reported, and the scoring key and the threshold separating high from low knowledge were not specified, which limits the reproducibility and interpretation of the overall knowledge comparisons. Differences in population, item wording and scoring also mean that comparisons with earlier surveys are descriptive.
5. Conclusion
Adults surveyed in Bisha recognized osteoarthritis as a chronic and common condition, and three-quarters identified aging as a risk factor. Substantial gaps remained: fewer than half identified cartilage degeneration as the underlying mechanism, 34.6% attributed the disease to cold or wet weather, 36.2% believed that blood tests are used for diagnosis, and 44.1% regarded acid-free diets and 49.5% intra-articular stem cell injection as effective treatments. No statistically significant association was found between knowledge category and sex, age or education level. Local health education should address these particular misconceptions, especially those concerning diagnosis and unproven treatments.
Declarations
Authors’ contributions. All authors contributed equally to all stages of the research work. All authors have read and agreed to the published version of the manuscript.
Conflict of interest. The authors declare that there is no conflict of interest regarding the publication of this article.
Funding. None.
Ethical approval and informed consent. The committee, approval reference and informed consent details are reported in Subjects and Methods.